What the Anion Gap Shows
The gap calculation is a derived number that assists clinicians in understanding acid-base status and detect underlying electrolyte disturbance. It is based on routine test values from a blood test and shows the difference between measured positively charged ions and negatively charged NAGMA causes ions in the blood.
In practice, the calculation uses sodium, chloride levels, and serum bicarbonate, with potassium sometimes included depending on the formula. The result gives insight into unmeasured anions that may be accumulating during illness. Because of that, the anion gap is a useful clinical tool for evaluating an acidotic state and narrowing the causes of metabolic acidemia.
Most clinicians first review a standard metabolic panel or a gas result when acid-base problems are suspected. The anion gap can then help determine whether the patient has increased anion gap metabolic acidosis or regular anion gap metabolic acidosis. That distinction matters because the underlying causes, severity, and next steps can be very different.
Although the calculation is simple, the interpretation is not. The value is only one piece of the broader medical interpretation of the patient’s condition. It should be considered alongside symptoms, medications, kidney function, glucose, lactate, ketones, and other test results.
How to Operate an Anion Gap Calculator
An anion gap calculator simplifies the gap calculation so you can quickly interpret the result from a blood chemistry panel. To use it, enter the serum sodium, chloride, and bicarbonate values. Some calculators also allow entry of albumin and potassium, which improves accuracy in certain cases.
The main advantage of a calculator is quickness and consistency. It cuts down on arithmetic mistakes and helps guide the evaluation of metabolic derangement. In many cases, the calculator will also display a corrected result if the serum albumin is low, since hypoalbuminemia can reduce the apparent gap and hide clinically important disease.
A practical workflow is as follows:
- Examine the basic metabolic panel or blood gas. Record serum sodium, serum chloride, and bicarbonate. Enter albumin if the calculator supports albumin correction. Compare the calculated anion gap against the expected reference interval. If the gap is elevated, assess for causes of metabolic acidosis. If the result is abnormal, consider whether a mixed acid-base disorder is present.
The calculator is most helpful when paired with the rest of the acid-base picture. A normal number does not automatically mean normal physiology, and an elevated number does not identify the cause by itself. It is a guide for further clinical interpretation, not a final diagnosis.
Anion Gap Equation & Normal Ranges
The classic anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians use potassium in the equation, but many modern calculators leave out it because the effect is small. When potassium is included, the result is slightly higher, but the same overall interpretive principles apply.
The normal anion gap varies with the lab method and the reference range reported by the laboratory. Different analyzers and measurement techniques can alter the expected interval. That is why it is best to interpret the result using the lab’s own reference interval rather than a universal cutoff alone.
Albumin correction is useful because serum albumin is a major unmeasured anion. When albumin is low, the anion gap may appear falsely normal. Correcting for albumin helps reveal a hidden increase in unmeasured anions. This can be especially important in critically ill patients with metabolic acidosis.
A common clinical approach is to raise the gap upward when albumin is below normal. The exact correction factor can vary by method, but the principle is the same: low albumin lowers the measured anion difference, so correction improves accuracy. For that reason, a good anion gap calculator often includes albumin correction as a built-in feature.
Understanding the formula also helps illustrate the physiology. The serum contains measured cations and anions, but not all ions are directly measured. The gap represents the difference created by these unmeasured anions, making it a helpful window into hidden metabolic processes.
What exactly delta gap Means and Why It’s Important
The delta gap extends the reading of the anion gap by comparing the increase in gap to the fall in bicarbonate. This comparison helps determine whether the patient has just one acid-base problem or a mixed acid-base disorder. It is especially useful in metabolic acidosis when the clinician wants to know if another process is also affecting the bicarbonate level.
This is where the delta-delta ratio enters the picture. The ratio measures the change in anion gap to the change in bicarbonate. If the ratio shows a mismatch, it may indicate an additional disorder such as metabolic alkalosis or another type of metabolic derangement occurring at the same time.
Why does this matter? Because not all cases of acidosis are clear-cut. A patient with high anion gap metabolic acidosis may also have vomiting, diuretic use, or other factors that push bicarbonate in the opposite direction. The delta gap and delta-delta ratio help expose those overlapping patterns.
In short, the delta gap is a delta calculation that gives more depth to the initial gap calculation. Instead of asking only whether the anion gap is elevated, it asks whether the increase in gap corresponds to the expected drop in bicarbonate. That makes it an important tool for acid-base interpretation.
Stepwise Delta Gap Calculation
To calculate the delta gap, initially find the measured anion gap from the chemistry values. Afterward compare it to the expected anion gap, which is often the upper end of the lab’s normal reference interval. The difference between the measured and expected values is the delta.
After that, compare that delta with the drop in bicarbonate. This comparison assists assess whether the bicarbonate loss is proportional to the increase in unmeasured acids.
A basic approach looks like this:
- Calculate the measured anion gap. Locate the expected anion gap from the lab reference range. Deduct expected from measured to find the delta gap. Assess that value with the change in bicarbonate. Analyze the pattern using the delta-delta ratio.
If the rise in anion gap is larger than the fall in bicarbonate, a second process such as metabolic alkalosis or preexisting elevated bicarbonate may be present. If bicarbonate falls more than expected, another acidifying process may be contributing. Either way, the result supports more nuanced acid-base interpretation.
This step-by-step approach is particularly useful when the clinical picture is unclear. For example, a patient may have metabolic acidosis from one source and vomiting-related alkalosis from another. A basic gap calculation alone may miss that combination, but the delta gap can point toward a mixed acid-base disorder.
How to Read Typical Findings
A increased anion gap metabolic acidosis typically suggests there is accumulation of organic acids or other unmeasured anions. A frequent clinical concern is not just whether the gap is high, but what is driving the rise and whether compensation is adequate.
In contrast, non-anion gap metabolic acidosis implies that bicarbonate has been depleted and substituted with chloride, so the gap remains within the reference interval. This pattern is often called hyperchloremic acidosis because chloride increases as bicarbonate decreases.
Respiratory compensation should also be checked. In metabolic acidosis, the body generally boosts ventilation to lower carbon dioxide and partially restore pH. A blood gas can help determine whether the compensatory response is appropriate or whether another respiratory disorder is present.
Common interpretive patterns include:
- High anion gap metabolic acidosis with expected ventilatory compensation. Normal-gap metabolic acidosis with hyperchloremia and bicarbonate loss. Metabolic acidosis with a superimposed combined acid-base disorder. Elevated gap with unexpected bicarbonate behavior suggesting a second process.
In clinical use, clinicians use the anion gap, delta gap, and blood gas in combination. The pattern is more meaningful than any single number. A patient can look clinically stable while having a significant hidden metabolic problem, or appear severely unwell with only small shifts in the measured gap.
Reasons of Raised Anion Gap
A broadened anion gap indicates build-up of unmeasured anions. A number of major conditions can lead to this pattern, and the differential diagnosis depends on the overall clinical picture, medications, and other lab findings.
Lactic acidosis is a frequent cause and may occur with tissue poor perfusion, sepsis, seizures, or severe illness. Elevated lactate introduces unmeasured acid to the blood and often results in high anion gap metabolic acidosis.
Diabetic ketoacidosis is a further classic cause. Ketone bodies build up and lower bicarbonate while increasing the gap. This is a key example of metabolic derangement where the anion gap calculator can rapidly highlight the severity of the acid-base problem.
Renal failure can also elevate the anion gap because the kidneys cannot excrete acid properly. Retained acids and reduced clearance of metabolic byproducts can contribute to the acidotic state.
Toxic alcohols are an significant and potentially dangerous cause. Methanol, ethylene glycol, and similar substances can generate acidic metabolites that increase the gap. In these cases, the gap may be only one clue among many, and urgent clinical assessment is essential.
Other causes may include medications, toxins, and inborn metabolic problems, but the major categories above are the most commonly emphasized. The key point is that an elevated anion gap signals a need to look for hidden acids, not simply to treat the number itself.
Etiologies of Normal Anion Gap Metabolic Acidosis
Normal anion gap metabolic acidosis typically indicates direct depletion of bicarbonate rather than increase of unidentified acids. Since the lost bicarbonate is offset by chloride, the serum chloride tends to increase, producing hyperchloremia.
Diarrhea is a common cause because the gastrointestinal tract can lose large amounts of bicarbonate-rich fluid. This causes metabolic acidosis with a normal gap and elevated chloride.
Renal tubular acidosis is another major cause. In this condition, the kidneys cannot process acid and bicarbonate properly, leading to persistent acid-base imbalance. Different forms of renal tubular acidosis can have different mechanisms, but they share the pattern of normal gap acidosis.
Bicarbonate loss can also occur through fistulas, certain medications, or renal causes. The common theme is that bicarbonate falls without a corresponding rise in unmeasured anions, so the anion gap may remain within range.
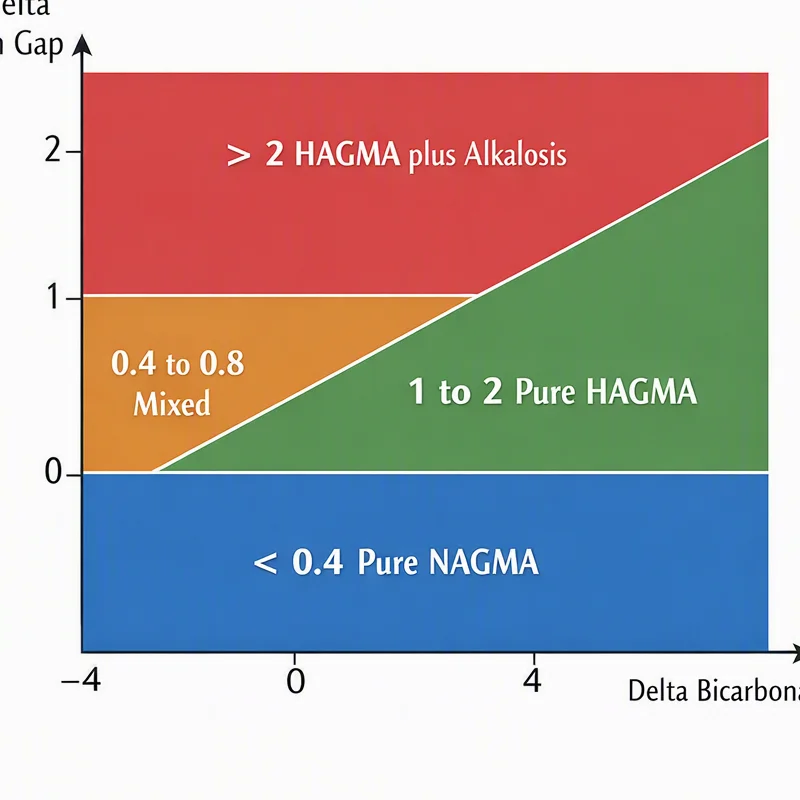
These patterns matter because they affect the workup. If the anion gap is normal, the next question chronic kidney disease anion gap is often whether the problem is gastrointestinal loss, renal tubular disease, or another cause of bicarbonate loss. The chloride level and blood gas results are especially helpful in that analysis.
Caveats and Clinical Caveats
Even a properly designed anion gap calculator has limitations. The biggest one is albumin correction. Because albumin is a important unmeasured anion, low serum levels can hide a true elevation in the gap. Without adjustment, a significant disorder may be missed.
Lab error is another caveat. Sample contamination, analyzer variation, or transcription mistakes can distort the result. If the value does not fit the clinical picture, repeat testing and review of the original basic metabolic panel may be necessary.
This calculated value also shows the overall acid-base balance at a single moment. It does not reveal how quickly the disorder developed or whether the patient is improving. Trends over time can be more informative than a single measurement.
Finally, clinical context is essential. A mildly abnormal anion gap in a stable patient has a different meaning than the same result in someone with shock, altered mental status, or kidney injury. The calculator aids judgment, but it does not replace it.
For best results, evaluate the anion gap, delta gap, and blood gas together, then compare them with symptoms, medications, and the rest of the chemistry profile. That holistic approach improves the chance of recognizing mixed acid-base disorder and determining the right underlying cause.
Frequently Asked Questions About Anion Gap and Delta Gap Calculators
What does an anion gap calculator used for?
An anion gap calculator is used to rapidly assess metabolic acidosis and identify whether the problem is likely to be a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis. It helps clinicians read electrolyte patterns from lab values and decide whether further evaluation is needed.
How is the delta gap determined?
To calculate the delta gap, first find the measured anion gap, then compare it with the expected anion gap from the lab’s reference interval. The difference is compared with the drop in bicarbonate. This helps determine whether there may be a mixed acid-base disorder.
Why does albumin affect the anion gap?
Albumin is a major unmeasured anion, so lower albumin reduces the apparent anion gap. That is why albumin correction matters. Without it, a true gap elevation may be missed, especially in patients with significant illness or low serum albumin.
What does a high anion gap mean?
A high anion gap commonly indicates there are additional unmeasured acids in the blood, such as those seen in lactic acidosis, diabetic ketoacidosis, renal failure, or toxic alcohols. It typically suggests metabolic acidosis and should be read with the blood gas and overall clinical picture.
Can a normal anion gap also suggest metabolic acidosis?
Yes, it can. Normal anion gap metabolic acidosis is not unusual and often results from diarrhea, renal tubular acidosis, or additional causes of bicarbonate loss. In this situation, chloride often rises to maintain electroneutrality, so the gap may remain normal even though the patient is acidotic.