How is defined the Anion Gap?
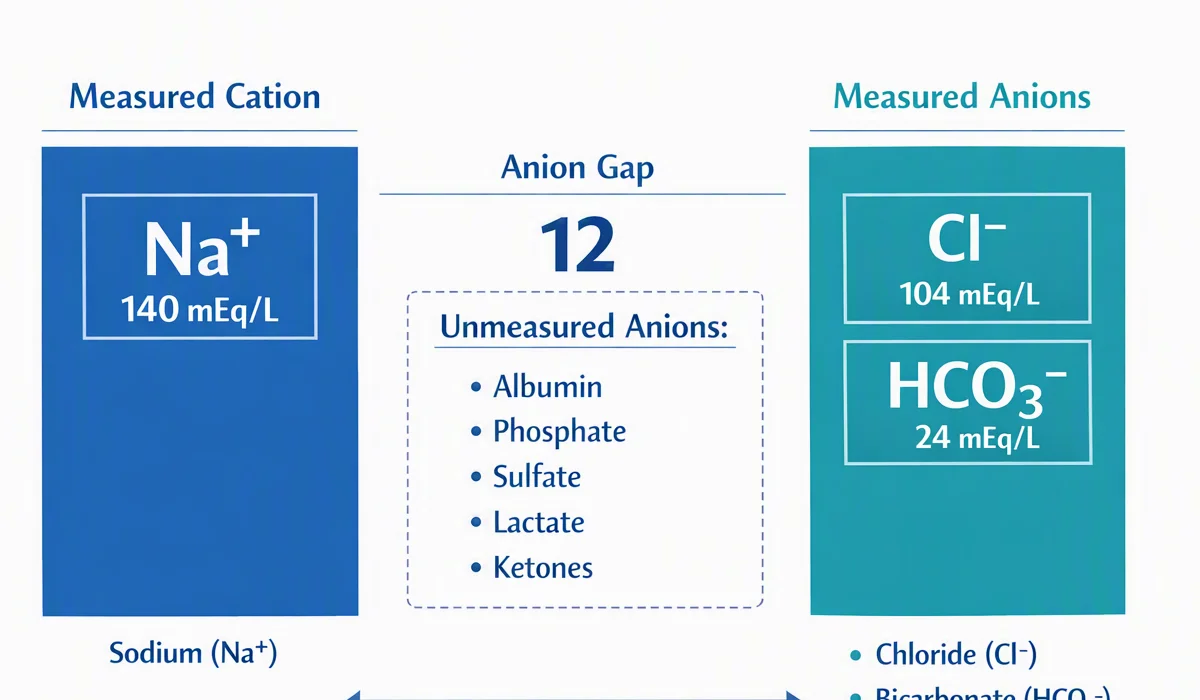
The anion gap is a derived value NAGMA causes that assists clinicians in understanding the balance between charged particles in the blood. It is usually obtained from routine electrolytes on a chemistry test, especially sodium and chloride, along with bicarbonate, to suggest whether there are extra acids in the bloodstream.
In plain language, the anion gap is part of lab interpretation for acid-base balance. A normal result shows the major charged particles are in expected balance, while an elevated result can point to an acid-base disorder such as metabolic acidosis. Because many acids are not directly measured, the gap acts as a diagnostic marker for hidden acid load, or unmeasured anions.
A standard anion gap calculator uses normal anion gap blood chemistry numbers from a serum chemistry panel or electrolyte panel. Most calculators focus on sodium, chloride, and bicarbonate, and some also include potassium. That makes the calculation a fast method to support clinical evaluation, but it does not substitute for a full medical assessment.
What Makes Kidney Disease Changes the Anion Gap
Kidney disease affects the anion gap because the kidneys normally help remove acid and keep stable serum electrolytes. When renal impairment limits that ability, the body may retain acid and acidic metabolic waste. Over time, this can lead to acid retention, acid accumulation, and ultimately systemic acidosis.
In chronic kidney disease, failing kidneys gradually forfeit the ability to excrete acids and regenerate bicarbonate. As bicarbonate declines, the blood’s buffer system deteriorates, which contributes to decreased bicarbonate and metabolic acidosis. At the same time, unmeasured acids can collect in the blood, causing an elevated anion gap.
These extra acids are often referred to as unmeasured anions because they are not directly shown on a routine panel. The increased gap indicates the presence of retained acids from reduced kidney clearance and abnormal metabolism. This is why the anion gap can be a helpful clue when evaluating kidney function and renal failure.
Kidney disease does not always produce the same pattern, though. Depending on the stage and cause, the dominant issue may be acid retention with extra unmeasured anions or a change in chloride handling that produces a normal-gap pattern. That is why the anion gap should be interpreted with the rest of the blood chemistry, not in isolation.
The Anion Gap during Initial vs Severe Kidney Disease
During the early stages of kidney disease, the glomerular filtration rate may be reduced only mildly, so the kidneys can still remove some acid. In this period, the anion gap may remain unchanged, or bicarbonate may begin to drift downward before the gap changes much. This is one reason early disease can be subtle on routine blood testing.
As kidney disease advances, uremia becomes more prominent and the body accumulates more metabolic waste. Uremic acids contribute to a increased anion gap because they behave like unmeasured anions. Advanced disease is therefore more likely to cause high anion gap metabolic acidosis, especially when renal function is significantly impaired.
The relationship between bicarbonate and the anion gap is important here. A falling bicarbonate level often signals worsening acid-base status, but the anion gap helps show whether the lost bicarbonate is being replaced by chloride or by retained acids. In other words, the gap helps distinguish the type of acidosis, not just its presence.
In some patients, advanced kidney disease can also occur with a normal anion gap pattern if chloride rises as bicarbonate falls. This makes the lab picture more complicated and highlights why clinicians review the full chemistry profile, including serum creatinine and blood urea nitrogen, before drawing conclusions about renal function.
How to Operate an Anion Gap Calculator
An anion gap calculator is a straightforward tool that calculates the gap from lab values commonly found on a serum chemistry panel. It typically requires sodium, chloride, and bicarbonate. Some formulas also add potassium, though many standard calculations exclude it because potassium is typically low in the blood compared with sodium.
To work with the calculator, enter the results from the blood test exactly as reported. The tool runs the anion calculation and gives a number that can be compared with the usual reference range used by the lab. A elevated number suggests extra unmeasured acids, while a typical number suggests the balance may be preserved or that bicarbonate loss is being offset by chloride.
This is where blood chemistry interpretation matters. The anion gap should be reviewed alongside other markers of kidney function such as serum creatinine and blood urea nitrogen, plus any signs of electrolyte imbalance. If the numbers suggest a problem, the calculator can prompt further clinical evaluation.
It is also important to understand that calculators are aids, not answers. They support pattern recognition, but the cause of an abnormal result still depends on symptoms, medical history, and the broader electrolyte panel. A calculator may indicate a possible issue with acid-base balance, but only a clinician can determine whether the pattern fits kidney disease, another acid-base disorder, or something else.
High Anion Gap vs Typical Anion Gap in Kidney Disease
Renal disease can lead to either increased anion gap metabolic acidosis or typical anion gap metabolic acidosis. The difference depends on what is happening to acids and chloride in the blood. In increased-gap states, acids are retained and accumulate as unmeasured anions. In typical-gap states, bicarbonate is lost or reduced, but chloride increases to compensate, producing elevated chloride.
Increased anion gap metabolic acidosis is more common when uremic acids build up in advanced kidney dysfunction. This pattern points to acid retention and reduced clearance of metabolic waste. It often suggests more severe renal impairment and may accompany rising serum creatinine and blood urea nitrogen.
Typical anion gap metabolic acidosis can happen earlier in the course of kidney disease or with certain tubular problems. In this setting, the body loses bicarbonate without a large increase in unmeasured acids. The result is a chloride rise that balances the charge, leading to a normal gap even though acidosis is still present.
The presence of hyperchloremia is a clue to this pattern. Because chloride rises as bicarbonate falls, the lab picture may show a “alteration” in the electrolyte balance rather than a clear elevation in the gap. This is why the same kidney problem can produce different results depending on stage and physiology.
Additional Sources of a High Anion Gap to Evaluate
Not all elevated gap is caused by kidney disease. A careful differential diagnosis is essential because other conditions can also cause metabolic acidosis. Among the most important are lactic acidosis, ketoacidosis, and ingestion of toxic alcohols.
Lactic acidosis happens when the body produces excess lactate, often due to impaired oxygen delivery, shock, severe infection, or other serious illness. Lactate is an unmeasured anion and can raise the gap even if kidney function is not the primary issue. In these cases, the blood chemistry may appear like uremic acidosis, so clinical context matters.
Ketoacidosis is another important cause. It can occur in diabetes, prolonged fasting, or heavy alcohol use. Ketones behave as unmeasured anions and raise the gap. Someone with kidney disease can also develop ketoacidosis, which makes interpretation more complex because more than one cause of acid-base disturbance may be present.
Toxic alcohols are also important to keep in mind in severe unexplained high-gap states. These exposures can create severe acid-base abnormalities and require urgent assessment. Because kidney disease may coexist with these problems, the anion gap should be viewed as one part of a broader workup rather than a standalone answer.
Whenever an Abnormal Anion Gap Calls for Medical Evaluation
An abnormal gap requires medical evaluation when it shows up with symptoms of acidosis or other alarming findings. Symptoms may include heavy or fast breathing, nausea, vomiting, confusion, fatigue, or increasing weakness. These signs can indicate impaired acid-base balance and possible electrolyte imbalance.
Within kidney disease, the overall picture counts. Elevated blood urea nitrogen and creatinine can suggest reduced kidney function, especially when paired with an abnormal anion gap. Once the chemistry panel also shows reduced bicarbonate, the suspicion for metabolic acidosis becomes greater. This is particularly important in people with known chronic kidney disease or acute kidney injury.
Acute kidney injury can cause a quick shift in acid regulation, sometimes more abruptly than ongoing kidney illness. The anion gap may rise rapidly if byproducts are retained and acid excretion drops. Because this can develop over hours and days, urgent clinical evaluation may be needed if the person feels ill or the lab changes are substantial.
When a person has kidney disease plus an unexpected lab result, the safest approach is immediate clinical review rather than waiting for signs to get worse. An abnormal gap can be an early sign of a severe acid-base disorder.
Clinicians usually check the complete blood chemistry, with serum creatinine, blood urea nitrogen, bicarbonate, sodium, chloride, potassium, and corresponding findings, before deciding on following steps. In line with the scenario, this may lead to repeat tests, treatment for acidosis, or assessment for another source of the abnormal result.
Common Questions Regarding Kidney Disease and Anion Gap
In what way does kidney disease affect the anion gap?
Kidney disease affects the anion gap by limiting the kidneys’ ability to clear acid and preserve acid-base balance. As renal function declines, acids and other unmeasured anions can accumulate, which may result in metabolic acidosis and an elevated anion gap. In some cases, chloride increases as bicarbonate falls, so the gap may stay normal even when acidosis is present.
Can chronic kidney disease always cause a high anion gap?
No. Chronic kidney disease does not necessarily cause a high anion gap. Early stages may show a normal gap or only mild changes in bicarbonate. A high anion gap is more likely when kidney function is more advanced and uremia results in more acid retention and buildup of unmeasured anions.
What is a normal anion gap mean in kidney disease?
A normal anion gap in kidney disease usually means the acidosis pattern is being offset by chloride, often called normal anion gap metabolic acidosis. This can happen when bicarbonate is lost or reduced without a large buildup of unmeasured acids. Hyperchloremia is often part of this pattern.
Can an anion gap calculator diagnose kidney disease?
No. An Anion Gap Calculator cannot diagnose kidney disease by itself. It is a tool for blood test interpretation and acid-base balance assessment. Diagnosis depends on the full clinical picture, including serum creatinine, blood urea nitrogen, symptoms, medical history, and other blood chemistry findings.
When ought an abnormal anion gap be checked by a doctor?
An abnormal anion gap should be checked by a doctor when it is new, severe, or occurs with symptoms of acidosis, electrolyte imbalance, confusion, breathing changes, or worsening illness. It should also be reviewed if kidney function is declining or if there is concern for lactic acidosis, ketoacidosis, toxic alcohol exposure, or acute kidney injury.